Most colon cancers do not appear suddenly. They start as a small, benign polyp that, in many cases, slowly turns into cancer over several years. This slow course, known as the adenoma-carcinoma sequence, is exactly why colonoscopy can not only diagnose cancer but also prevent it.
At a glance
- Most colon cancers develop from polyps, through a slow progression that usually takes about a decade.
- Not all polyps become cancer. What matters most are adenomas and certain serrated lesions.
- Size (10 millimeters or larger), villous histology and high-grade dysplasia increase the risk of progression.
- Removing polyps during colonoscopy interrupts the sequence. Large studies show a substantial reduction in both the occurrence of cancer and deaths from it.
What is the adenoma-carcinoma sequence?
The vast majority of colon cancers are sporadic and are not inherited. They develop gradually, as the normal lining of the bowel (mucosa) passes through successive stages: from a small adenoma, to an advanced adenoma and, finally, to carcinoma. This model, first described in the 1970s, is called the adenoma-carcinoma sequence and is a fundamental concept for prevention.
The progression usually takes about a decade, and removing the polyp interrupts it.
Time is the key. The transition from an adenoma to cancer is slow and usually takes about a decade. This window of years is what allows screening to find and remove lesions before they become dangerous.
Not all polyps become cancer
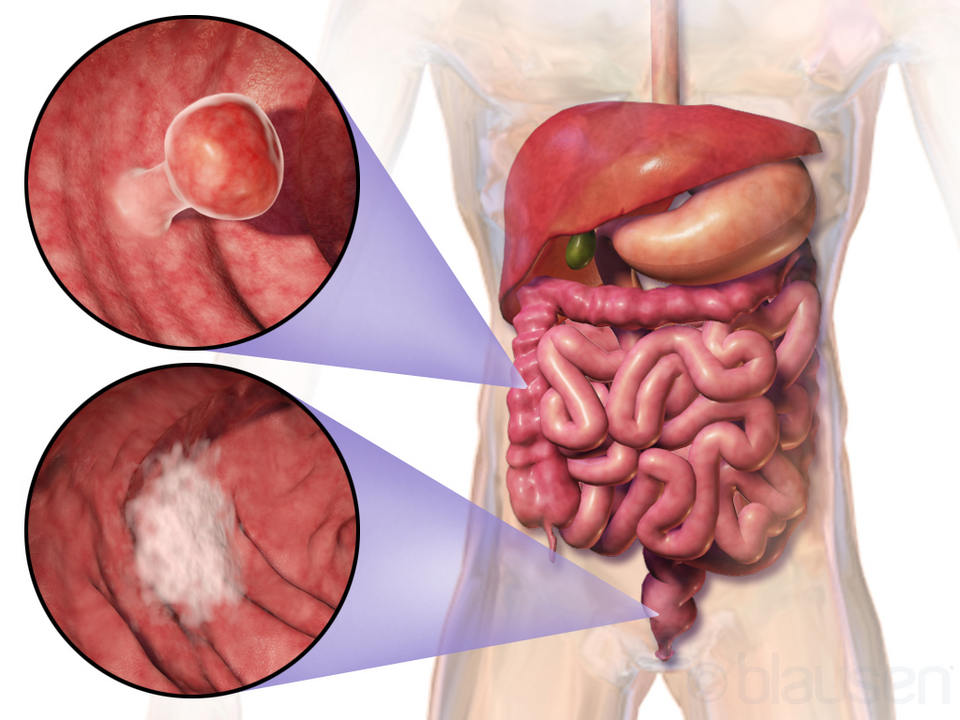
A polyp is a growth that protrudes from the lining of the bowel. It is a common finding: about one in four people over the age of 50 has at least one. The vast majority will never become cancer. What matters is the type of polyp.
Adenomas
These are the precancerous polyps of the classic sequence. Histologically, they are divided into tubular, tubulovillous and villous adenomas. Villous adenomas are significantly more likely to progress to cancer than tubular ones.
Serrated lesions
This is a second category with its own distinct behavior. Hyperplastic polyps are usually harmless, but sessile serrated lesions and serrated adenomas have the potential to become malignant and account for a proportion of colon cancers.
| Polyp type | Malignant potential |
|---|---|
| Tubular adenoma | Precancerous · lower risk |
| Tubulovillous / villous adenoma | Precancerous · higher risk |
| Hyperplastic polyp | Usually benign |
| Sessile serrated lesion | Precancerous |
| Serrated adenoma | Precancerous · rare |
What makes a polyp more dangerous
Not all adenomas carry the same risk. Certain features classify a polyp as an advanced adenoma, meaning it has a higher chance of progressing to cancer:
- Size of 10 millimeters or larger
- Villous histology
- High-grade dysplasia (marked cell changes)
- Multiple polyps (typically three or more)
The larger the polyp, the higher the chance that it already contains areas of cancer. That is why the histological examination after removal is crucial: it determines the type, the degree of dysplasia and the follow-up plan.
The second pathway: serrated lesions
Beyond the classic sequence, there is also a second pathway to cancer. The so-called serrated pathway accounts for a significant percentage of cases. These lesions are often flat and pale, are usually located on the right side of the colon and are harder to recognize with the naked eye.
This is one of the reasons why the quality of colonoscopy matters so much: a careful, complete examination of the bowel and the right technique increase the chance of detecting these less visible lesions as well.
Why colonoscopy stops the sequence
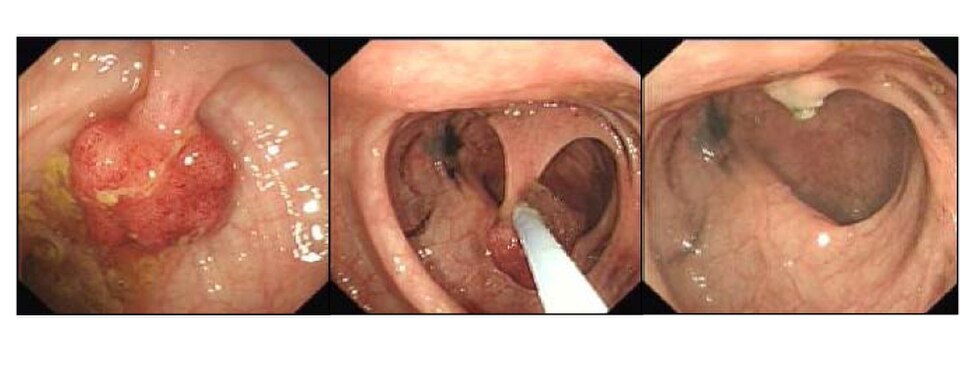
This is the unique value of colonoscopy: it is not only diagnostic but also therapeutic and preventive. By finding and removing polyps in the same session (polypectomy), it interrupts the sequence before it is completed.
The benefit of this intervention is well documented. Landmark follow-up studies showed that removing adenomas during colonoscopy drastically reduces the occurrence of colon cancer, while long-term data have also documented a significant reduction in deaths from the disease.
Proper colonoscopy preparation is crucial, because a clean bowel allows the doctor to see even the smallest or flat lesions.
Symptoms: why waiting for them is not enough
Most polyps, as well as the early stages of colon cancer, cause no symptoms. When symptoms do appear, such as blood in the stool, a change in bowel habits or anemia, the lesion may already be at an advanced stage.
This is exactly why screening is aimed at people without symptoms. We do not wait for a warning sign before we check. We check so that we get ahead of the warning sign.
After removal: follow-up
Removing a polyp does not always mean the story is over. Because new polyps can appear over time, a follow-up program with repeat colonoscopy is set up. The interval is tailored to the number, size and histological type of the polyps removed, and usually ranges from a few to several years.
In people with multiple or advanced polyps, a family history or inflammatory bowel disease, follow-up is closer and is determined by the gastroenterologist.
Frequently asked questions
Book your appointment with Dr. Thomaidis
Do you have a history of polyps, or would you like a screening check-up? A timely, specialized colonoscopy finds and removes lesions before they progress. Contact us today to schedule your appointment.
Send your request
Fill in your details and we will contact you to schedule your appointment.
Sources
- NHS – Bowel polyps. nhs.uk
- NICE – Suspected cancer: recognition and referral (NG12). nice.org.uk
- ESGE – Post-polypectomy colonoscopy surveillance: ESGE Guideline. esge.com
- American Cancer Society – Colorectal Cancer Screening Guideline. cancer.org

About the doctor
Dr. Thomas Thomaidis, MD, PhD – Interventional Gastroenterologist. Associate Professor of Gastroenterology specializing in diagnostic and therapeutic endoscopy, member of international scientific societies (ASGE, DGVS, Hellenic Society of Gastroenterology). View the full CV.
Book an appointment for a diagnostic check-up.
This article is for informational purposes only and does not replace individualized medical advice, diagnosis or treatment. For your own check-up and follow-up plan, please consult a doctor.
Content last updated: October 2026 (12/10/2026).